The First-Fill Penalty: What Pharmacy Transfers Really Cost and How to Protect Your Wallet

Photo: U.S. Navy photo by Chief Warrant Officer 4 Seth Rossman., Public domain, via Wikimedia Commons
The Assumption That Costs Patients Money
Most Americans assume that moving a prescription from one pharmacy to another is a neutral transaction—a simple administrative handoff that carries no financial consequence. The medication is the same, the dosage is the same, and in many cases the insurance plan is identical. So why does the bill at the new counter so often come out higher?
The answer lies in a combination of pharmacy system mechanics, insurance adjudication protocols, and pricing algorithms that collectively penalize patients for changing where they fill their prescriptions. At RxPriceWatch, we refer to this phenomenon as the first-fill penalty—a cluster of charges and price adjustments that tend to surface precisely when a patient transfers a prescription to an unfamiliar location.
Understanding how this penalty works is the first step toward avoiding it.
How Pharmacy Pricing Systems Treat New Patients
When you fill a prescription at a pharmacy where you have an established history, that location's internal system recognizes you. It has a record of your insurance information, your prior authorization status, and—critically—the reimbursement rates your plan has negotiated for your specific medications. That history allows the system to process your refill quickly and at a predictable price.
At a new pharmacy, none of that context exists. The system must build your profile from scratch, and during that initialization process, several things can go wrong from a pricing standpoint.
First, the new pharmacy must submit a fresh claim to your insurance carrier. While this sounds routine, insurance adjudication systems sometimes flag first-time submissions from a new dispensing location for additional review. That review can temporarily default your prescription to a higher pricing tier until your plan confirms coverage details—a process that may take one billing cycle to resolve.
Second, some pharmacy benefit managers (PBMs) treat a transfer as the start of a new dispensing episode. Depending on how your plan's accumulator or deductible logic is structured, this can affect how much of the drug's cost is applied to your out-of-pocket maximum, occasionally resetting certain cost-sharing calculations in ways that disadvantage the patient.
The Role of Inventory and Dispensing Fees
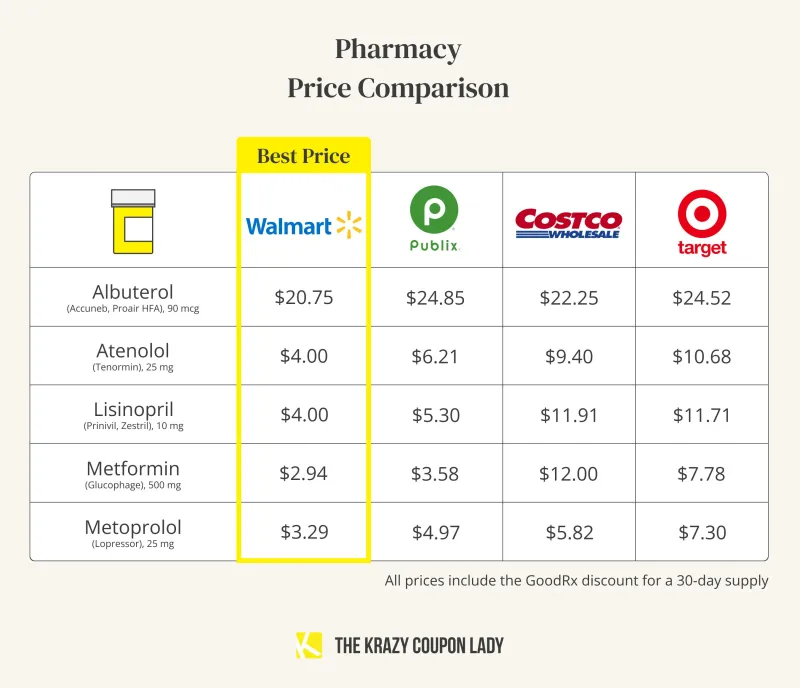
Beyond insurance mechanics, pharmacies themselves impose charges that aren't always visible on the receipt. Dispensing fees—administrative costs built into the final price of a prescription—can vary substantially between pharmacy chains, independent locations, and mail-order services. When you transfer, you move into the fee structure of the new provider, which may be meaningfully higher than what you were paying before.
Some pharmacies also impose what are informally called inventory acquisition surcharges on lower-volume medications. If the drug you're transferring isn't a high-turnover item at the new location, that pharmacy may have sourced it at a higher wholesale price than your previous provider. That cost difference frequently flows downstream to the patient, particularly for specialty medications or drugs with limited generic competition.
For patients on maintenance medications—prescriptions they fill every 30 to 90 days on an ongoing basis—even a modest per-fill surcharge compounds significantly over the course of a year.
How Transfer Data Influences Future Pricing
One of the less-discussed dimensions of pharmacy transfers is the way transaction data shapes subsequent pricing. Major pharmacy chains use sophisticated data systems that track not only what drugs are dispensed, but how patients arrive at their counters. A prescription transferred from a competitor signals a degree of price sensitivity or dissatisfaction—information that some systems use to calibrate promotional pricing, discount eligibility, and coupon targeting.
In practice, this means that patients who transfer frequently may receive fewer proactive discount offers from their new pharmacy, because the system has flagged them as mobile customers who may not remain long-term. Conversely, long-standing customers at a single location sometimes benefit from pricing stability that isn't explicitly advertised but is embedded in how the pharmacy handles their claims.
This dynamic is difficult to quantify precisely because pharmacy pricing algorithms are proprietary. However, the pattern is consistent enough that pricing researchers and patient advocates have noted it repeatedly in studies of retail pharmacy behavior.
When Transfers Make Financial Sense Despite the Upfront Cost
None of this is to suggest that patients should never transfer their prescriptions. There are circumstances in which the long-term savings at a new pharmacy outweigh the short-term first-fill penalty.
If you are moving to a pharmacy that participates in a lower pricing tier under your insurance plan, the reduced copay on subsequent fills will eventually offset the initial cost spike. Similarly, if you are switching from a retail pharmacy to a mail-order service endorsed by your PBM, the 90-day supply discount typically available through those channels can produce meaningful savings over time—even if the first shipment costs more than expected.
The key is to perform the calculation before you transfer, not after.
A Step-by-Step Guide to Minimizing Transfer Penalties
Patients who approach pharmacy transfers strategically can reduce or eliminate the first-fill penalty in most cases. The following steps are worth taking before initiating any transfer:
1. Call your insurance plan first. Ask specifically whether your plan treats a transfer to a new dispensing location as a new claim episode. Request clarification on whether any deductible or accumulator resets apply. Get the representative's name and note the date of the call.
2. Ask the new pharmacy for a price quote before transferring. Most pharmacies will provide a cash-price estimate and an insurance-estimated cost if you provide your plan information in advance. Compare this to what you currently pay.
3. Request that the new pharmacy verify your prior authorization status. If your medication requires prior authorization, confirm that the new location can retrieve that authorization from your insurer before your first fill. A lapsed or unverified authorization is one of the most common causes of unexpected first-fill price increases.
4. Time your transfer strategically. Transferring early in a billing period—rather than mid-cycle—can reduce the likelihood of adjudication anomalies. It also gives you time to address any pricing discrepancies before your next scheduled refill.
5. Ask about dispensing fee structures explicitly. Pharmacies are not always forthcoming about how their dispensing fees are calculated, but they are required to disclose them upon request. A difference of even two or three dollars per fill adds up over a year of maintenance medication use.
6. Monitor your Explanation of Benefits (EOB). After your first fill at the new location, review the EOB your insurer generates. Compare it to prior EOBs from your previous pharmacy. Discrepancies in how the claim was adjudicated are often easier to dispute in the weeks immediately following the transaction.
The Bigger Picture
Pharmacy transfers are a routine part of American healthcare—people move, insurance plans change, and discount programs emerge that make switching financially attractive. But the infrastructure surrounding prescription dispensing was not designed with patient transparency as its primary objective. Fees are embedded in prices, insurance systems reset without notice, and algorithms quietly adjust what individual patients pay based on behavioral data.
At RxPriceWatch, our position is straightforward: patients deserve to know the full cost of a transaction before they commit to it. The first-fill penalty is real, it is measurable, and in most cases it is avoidable—provided patients have the information they need to act before the transfer is complete rather than after the receipt has printed.